
UNIT 1.5 · BIOLOGICAL BASES OF BEHAVIOR
Sleep — AP Psychology Study Notes
Compare NREM and REM sleep, explain circadian rhythms, and apply dream theories and sleep-disorder concepts.

Topic overview
Humans spend roughly one-third of their lives sleeping, yet sleep remains one of psychology's most fascinating mysteries.
Sleep is not simply the absence of consciousness but rather an altered state of consciousness characterized by reduced awareness, reversibility, and essential restorative functions.
Understanding sleep cycles, stages, theories, and disorders helps explain how sleep affects memory consolidation, emotional regulation, physical health, and daily performance.
Consciousness and Awareness
What is Consciousness?
Consciousness is our awareness of ourselves and our environment, including thoughts, feelings, sensations, and external stimuli.
Consciousness exists on a continuum from high awareness (fully awake and alert) to low awareness (deep sleep or unconsciousness).
Levels of Consciousness
| State | Level of Awareness |
|---|---|
| Fully Awake | High awareness; focused attention on surroundings |
| Drowsy | Reduced awareness; thoughts drift, attention fades |
| Light Sleep | Low awareness; some sounds still registered |
| Deep Sleep | Minimal awareness; external stimuli mostly ignored |
Key Point: Sleep is NOT the absence of consciousness—it's a different, altered state where the brain remains active with reduced external awareness.
Circadian Rhythm: The Body's Clock
What is Circadian Rhythm?
The circadian rhythm is the body's internal biological clock that operates on an approximately 24-hour cycle, regulating sleep-wake patterns, body temperature, hormone release, and alertness.
Key Control Center: The suprachiasmatic nucleus (SCN) in the hypothalamus controls circadian rhythms.
- Light exposure is the primary cue (zeitgeber) that synchronizes the internal clock with the 24-hour day
- Light → retina → SCN → pineal gland → regulates melatonin production
- Darkness triggers melatonin release → signals sleepiness
- Light suppresses melatonin → promotes wakefulness
Circadian Rhythm Effects on Behavior
Daily Pattern:
- Morning: Temperature, alertness and hormonal patterns change with biological time; a fixed 6–7 AM wake peak is not universal.
- Daily alertness: Timing varies with chronotype, age, prior sleep and schedule. There is no universal clock-time peak for everyone.
- Afternoon (2 PM – 3 PM): Natural energy dip (post-lunch slump)
- Evening: A circadian alerting signal can oppose sleep pressure before habitual bedtime; its timing varies.
- Biological night: Melatonin rises under dim conditions at an individually timed phase; it is a timing signal, not an on/off sleep switch.
Circadian Rhythm Disruptions
| Disruption | Cause | Effects |
|---|---|---|
| Jet Lag | Rapid travel across time zones | Insomnia, fatigue, mood swings, digestive issues |
| Shift Work | Working night shifts or irregular hours | Difficulty sleeping, reduced alertness, health problems |
| Screen Exposure | Blue light from devices suppresses melatonin | Delayed sleep onset, poor sleep quality |
The Sleep Cycle
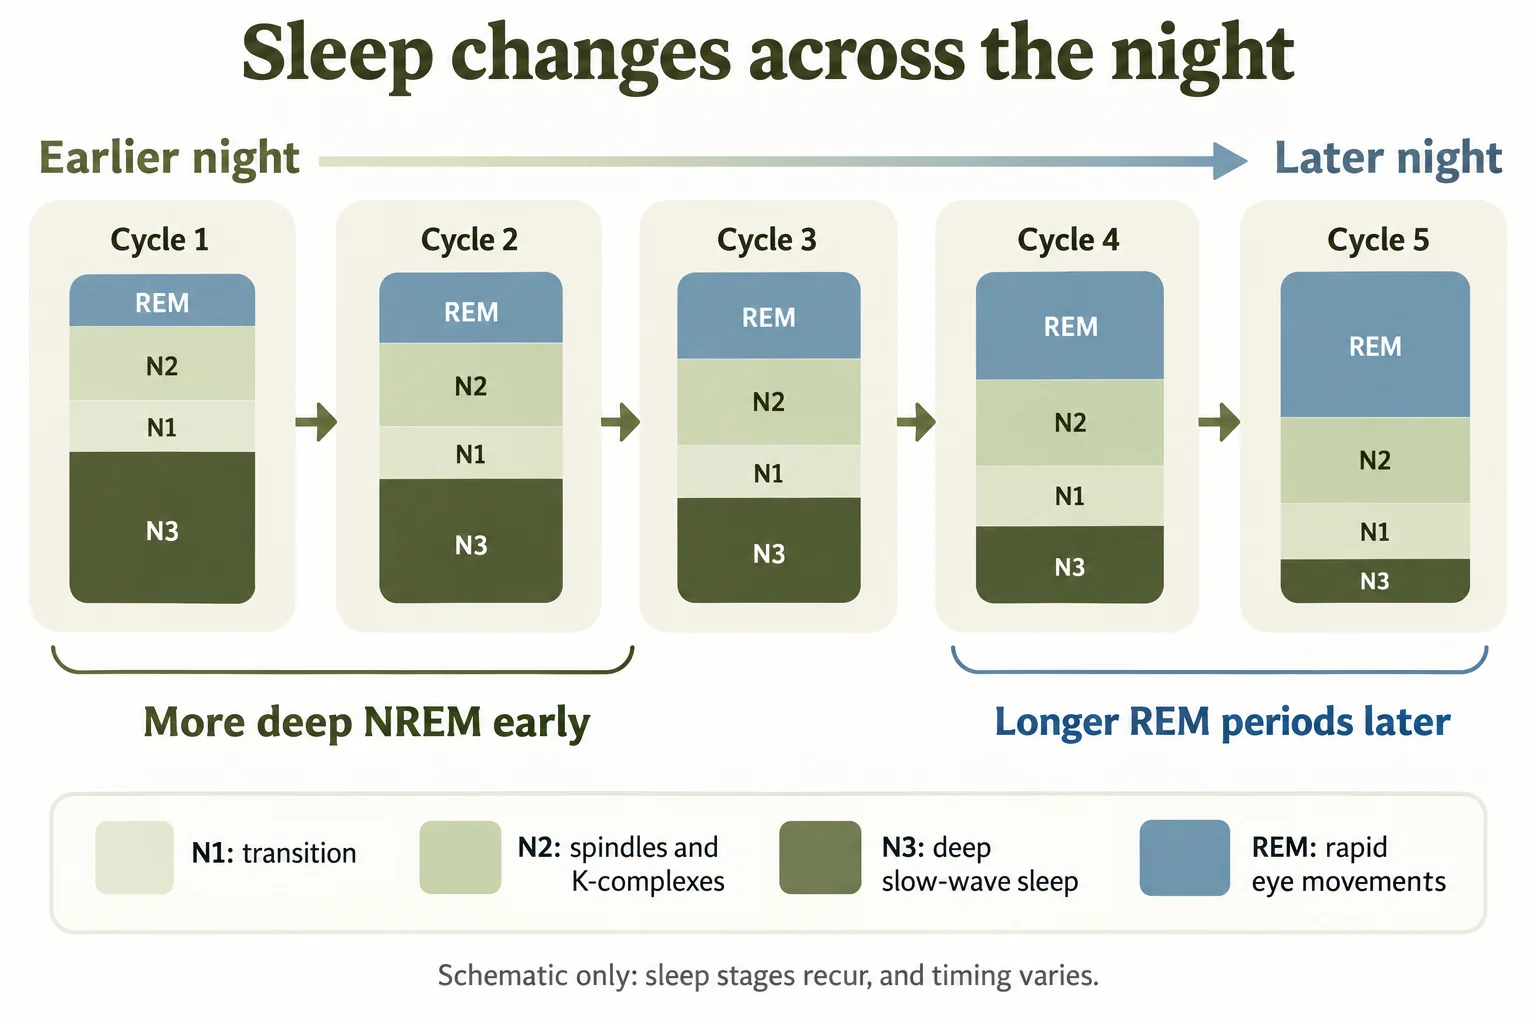
Sleep Cycle Structure
Sleep usually cycles repeatedly between NREM and REM. A cycle often takes roughly 80–100 minutes and can vary considerably; four to six cycles can occur in an adult night. This is a typical pattern, not a fixed schedule for every person or cycle.
Typical progression: N1 begins sleep, followed by N2 and often N3, then a return toward lighter NREM before REM. Later cycles commonly contain less N3 and longer REM periods; brief awakenings can occur.
Important Pattern: As the night progresses, Stage 3 (deep sleep) decreases while REM sleep increases in duration.
NREM Sleep (Non-Rapid Eye Movement)
NREM sleep has three stages, N1, N2 and N3, distinguished by physiological and EEG features. NREM and REM both contribute to memory and other functions; the pattern is not a simple split between body repair and brain repair.
Stage 1 NREM: Light Sleep (Transition)
Stage 1 is the lightest phase of sleep, the brief transition from wakefulness to sleep lasting only a few minutes.
Characteristics:
- EEG Pattern: Theta waves (slower brain activity than wakefulness)
- Duration: 1-5 minutes
- Easily awakened from this stage
- Hypnagogic sensations — brief, dream-like images, floating feelings, sudden body jerks (hypnic jerks), or the sensation of falling
- Muscles begin to relax; heartbeat and breathing slow
Hypnagogic Sensations
Definition: Brief, dreamlike hallucinations or sensations that occur during the transition from wakefulness to Stage 1 sleep (falling, floating, sudden jerks).
Stage 2 NREM: Deeper Light Sleep
Stage 2 is a deeper sleep where the body prepares for slow-wave sleep, accounting for about 50% of total sleep time.
Characteristics:
- EEG Pattern: Sleep spindles (brief bursts of rapid brain activity) and K-complexes (large, slow waves)
- Duration: 10-25 minutes in first cycle; increases with each cycle
- Body temperature drops
- Heart rate slows
- Less awareness of surroundings
- Sleep spindles help shield the brain from external disturbances and are important for memory consolidation
EEG Markers
Sleep Spindles: Rapid bursts of brain waves that protect sleep from disturbances
K-Complexes: Large, slow waves that help maintain sleep and may play a role in memory processing
Stage 3 NREM: Deep Sleep (Slow-Wave Sleep)
Stage 3 is the deepest NREM sleep stage, also called slow-wave sleep (SWS), where the most restorative physical processes occur.
Characteristics:
- EEG Pattern: Delta waves (slow, high-amplitude brain waves)
- Duration: Longest early in the night; decreases with each cycle
- Very difficult to wake someone in this stage
- If awakened, person feels groggy and disoriented (sleep inertia)
- Physical restoration: Tissue repair, muscle growth, immune system strengthening
- Energy replenishment: Body restores energy reserves
- Hormone release: Growth hormone secretion peaks
Key Functions: Stage 3 is critical for physical health, immune function, and feeling refreshed the next day. Most deep sleep occurs in the first half of the night.
REM Sleep (Rapid Eye Movement)
Paradoxical Sleep
REM sleep is called "paradoxical sleep" because the brain is highly active (similar to waking EEG patterns) while the body is in its most relaxed state.
Characteristics:
- EEG Pattern: Low-amplitude mixed-frequency activity, resembling waking in some respects
- First REM period: Occurs about 90 minutes after falling asleep
- REM periods lengthen as the night progresses; longest REM occurs in the early morning
- Rapid eye movements under closed eyelids
- Muscle atonia: Most skeletal muscles show strongly reduced tone during REM. Eye movements and breathing continue; it is not paralysis of every muscle.
- Vivid, story-like dreams most commonly occur during REM
- Increased heart rate and breathing (can be irregular)
REM Sleep Functions
- Memory consolidation: Especially for procedural (skills) and emotional memories
- Emotional regulation: Processing and integrating emotions from the day
- Brain development: Critical in infancy and childhood for neural connections
- Creative problem-solving: May facilitate insight and novel connections
- Dreaming: Most vivid dreams occur in REM sleep
REM Rebound
REM rebound occurs when someone is deprived of REM sleep (from alcohol, medication, or sleep disruption) and then compensates by spending more time in REM during subsequent sleep periods.
The brain prioritizes catching up on lost REM sleep, entering REM more quickly and staying in it longer, demonstrating REM's importance for cognitive and emotional functioning.
NREM vs. REM Sleep Comparison
| Feature | NREM Sleep | REM Sleep |
|---|---|---|
| Brain Activity | Slows progressively (theta → delta waves) | Low-amplitude mixed-frequency activity, resembling waking in some respects |
| Body State | Relaxed muscles, slowed breathing and heart rate | Muscle atonia (paralysis), rapid eye movements |
| Primary Function | Physical restoration, tissue repair, immune function | Memory consolidation, emotional regulation, dreaming |
| Dreams | Can occur but are less vivid and less common | Vivid, story-like, emotional dreams |
| Timing | Dominates first half of night (esp. Stage 3) | Increases in duration as night progresses |
Theories of Sleep Function
Why do we sleep? Several theories explain the biological and psychological purposes of sleep.
1. Restoration Theory
Restoration theory proposes that sleep allows the body and brain to repair and restore themselves after daily wear and tear.
Key Ideas:
- Sleep repairs cells and tissues
- Sleep clears metabolic waste from the brain (including toxins that accumulate during waking hours)
- Sleep replenishes energy reserves
- Sleep strengthens the immune system
- Sleep influences neurotransmission and neural regulation; it is not a uniform reset to one fixed transmitter level.
Evidence: Sleep deprivation leads to impaired physical performance, weakened immune response, and cognitive decline.
2. Memory Consolidation Theory
Memory consolidation theory suggests that sleep helps the brain organize, process, and store memories from the day.
Key Ideas:
- During sleep, the brain replays and reorganizes daily experiences
- Neural pathways are strengthened for important memories
- Unnecessary connections are pruned to increase efficiency
- Information transfers from hippocampus to long-term cortical storage
- Emotions are integrated and regulated
Evidence: Studies show better memory retention and learning after sleep. Sleep deprivation impairs memory formation and recall.
3. Evolutionary (Adaptive) Theory
Optional background: adaptive accounts. Different sleep patterns may reflect ecological pressures and energy conservation. A simple claim that all species sleep to hide from nighttime predators cannot explain every pattern; restoration and consolidation are the central accounts emphasized here.
Key Ideas:
- Sleep kept early humans inactive and hidden during darkness when predators were most active
- Sleep conserves energy when food-gathering isn't possible (nighttime)
- Different species have different sleep patterns based on their ecological niche
Example: Prey animals (like rabbits) sleep lightly and briefly; predators (like lions) sleep deeply and longer.
Theories of Dreaming
Why do we dream? Two major theories tested on the AP Psychology exam explain dream function.
Important Exam Note
Freud's Psychoanalytic Dream Theory (dreams as wish fulfillment, manifest/latent content) is NOT tested on the AP Psychology exam. Only focus on the two theories below.
1. Activation-Synthesis Theory
The activation-synthesis theory (proposed by Hobson and McCarley) suggests that dreams are the brain's attempt to make sense of random neural firing that occurs during REM sleep.
How It Works:
- During REM, the brainstem (pons) generates random neural activity
- The cerebral cortex tries to synthesize this random activity into a coherent narrative
- The brain creates a story from scattered signals — memories, emotions, sensations
- This explains why dreams often feel bizarre, illogical, or disjointed
Key point: Activation-synthesis explains dreams as the cortex organizing internally generated activity. It does not prove that every dream is personally meaningless, nor that dreaming occurs only in REM.
2. Memory Consolidation Theory (Information Processing)
The memory consolidation theory proposes that dreaming serves a purposeful function — helping the brain process, organize, and store daily experiences and emotions.
How It Works:
- Dreams help sort and file information from the day
- Important memories are strengthened; unimportant ones are pruned
- Emotional experiences are processed and integrated
- Dreams act like the brain's overnight filing system
Key point: Consolidation accounts connect sleeping brain activity and dream content with memory processing. Evidence that sleep helps memory does not establish a unique purpose for every dream or a symbolic meaning for each detail.
Dream Theory Comparison
| Theory | Dream Purpose | Key Idea |
|---|---|---|
| Activation-Synthesis | Synthesis of internally generated activity | Brain makes sense of random neural firing from brainstem |
| Memory Consolidation | Possible links with processing and consolidating experience | Brain processes daily experiences and strengthens memories |
Sleep Disorders
Sleep disorders disrupt natural sleep cycles and significantly affect physical health, cognitive performance, and emotional well-being.
AP Exam Coverage
The AP Psychology exam covers ONLY these five sleep disorders. These are the five disorders in the current AP content scope; other sleep disorders exist.
1. Insomnia
Insomnia is the most common sleep disorder, characterized by persistent difficulty falling asleep, staying asleep, or both.
Symptoms:
- Persistent difficulty initiating sleep, despite an adequate opportunity to sleep; one long night alone is not a diagnosis
- Difficulty maintaining sleep (frequent night awakenings)
- Waking up too early and unable to return to sleep
- Daytime fatigue, irritability, poor concentration
Causes: Stress, anxiety, poor sleep habits, caffeine, screen exposure before bed
Treatment: Cognitive-behavioral therapy (CBT-I), sleep hygiene, relaxation techniques
2. Narcolepsy
Narcolepsy is a neurological disorder characterized by sudden, uncontrollable sleep attacks during the day.
Symptoms:
- Excessive daytime sleepiness — overwhelming urge to sleep
- Sleep attacks — falling asleep suddenly and involuntarily (can happen while driving, eating, talking)
- Cataplexy — sudden muscle weakness triggered by strong emotions (laughter, surprise)
- Entering REM sleep abnormally quickly
- Fragmented nighttime sleep
Biological context: Loss of orexin/hypocretin signaling is characteristic of narcolepsy type 1. Cataplexy is not present in every case, and type 2 narcolepsy differs. Sudden sleep episodes are not the only defining difficulty: persistent daytime sleepiness is central.
Treatment: Individualized clinical care can include medication and planned sleep schedules
3. Sleep Apnea
Sleep apnea is a disorder where breathing repeatedly stops and starts during sleep, causing brief awakenings that disrupt sleep cycles.
Symptoms:
- Loud snoring (often noticed by bed partner)
- Pauses in breathing followed by gasping or choking sounds
- Frequent awakenings (person may not remember them)
- Daytime sleepiness despite spending enough time in bed
- Morning headaches, dry mouth
Effects: Fragmented sleep reduces Stage 3 and REM sleep; increases risk of heart disease, stroke, high blood pressure
Treatment: Clinician-selected options may include positive-airway-pressure therapy, oral appliances and other measures depending on apnea type and cause
4. REM Sleep Behavior Disorder
REM sleep behavior disorder occurs when the normal muscle atonia (paralysis) during REM sleep is absent, allowing people to physically act out their dreams.
Symptoms:
- Acting out dreams — punching, kicking, shouting, flailing arms
- Can injure self or bed partner
- Person usually remembers the dream upon waking
- More common in older adults, particularly men
Cause: Breakdown of brainstem mechanisms that normally paralyze muscles during REM
Treatment: Clinical evaluation, an individualized management plan and measures to reduce injury risk
5. Somnambulism (Sleepwalking)
Somnambulism (sleepwalking) involves walking or performing complex behaviors during deep NREM sleep (Stage 3) without conscious awareness.
Symptoms:
- Walking during sleep with eyes open but blank expression
- Performing activities (getting dressed, eating, leaving the house)
- Difficult to awaken; if awakened, person is confused and disoriented
- No memory of the episode upon waking
- More common in children (outgrow it in adolescence)
Triggers: Sleep deprivation, stress, fever, medications, irregular sleep schedules
Safety Note: Contrary to myth, it is NOT dangerous to wake a sleepwalker — gently guide them back to bed
Treatment: Improve sleep hygiene, maintain regular sleep schedule, secure environment (lock doors, remove obstacles)
Sleep Disorders Quick Reference
| Disorder | Main Symptom | Sleep Stage |
|---|---|---|
| Insomnia | Difficulty falling or staying asleep | All stages affected |
| Narcolepsy | Sudden, uncontrollable sleep attacks | Rapid entry into REM |
| Sleep Apnea | Breathing interruptions during sleep | Disrupts all stages |
| REM Sleep Behavior Disorder | Acting out dreams (no muscle paralysis) | REM sleep |
| Somnambulism | Sleepwalking without awareness | Stage 3 NREM (deep sleep) |
Use these descriptions to compare concepts: Symptoms can overlap and diagnosis depends on clinical criteria, not one isolated example. Narcolepsy is different from REM sleep behavior disorder; sleepwalking usually arises from N3. Gentle awakening is not inherently dangerous, but safety and calm guidance matter.
Sleep and Memory Consolidation
Sleep is essential for learning and memory formation. Both NREM and REM sleep play critical roles in consolidating different types of memories.
How Sleep Strengthens Memory:
- The brain replays and reorganizes daily experiences during sleep
- Neural pathways are strengthened for important memories
- Synaptic connections are pruned for unimportant information
- Waste products are cleared from the brain
- Neurotransmission and neural regulation change across sleep and waking states; there is no single universal reset level.
Effects of Sleep Deprivation
Lack of sleep severely impairs cognitive, emotional, and physical functioning.
Cognitive Effects:
- Impaired attention and focus
- Memory problems — difficulty forming new memories and recalling old ones
- Slower reaction time
- Poor decision-making and judgment
- Reduced creativity and problem-solving
Physical & Emotional Effects:
- Weakened immune system — increased illness risk
- Irritability, mood swings
- Increased anxiety and depression
- Weight gain (disrupted hunger hormones)
- Higher risk of accidents and injuries
Study Tip: Research shows it's better to review material and get sleep than to pull an all-nighter before a test. Sleep consolidates what you studied!
AP Exam Strategy
Multiple Choice Tips
- Master EEG patterns: theta (Stage 1), sleep spindles/K-complexes (Stage 2), delta (Stage 3), low-amplitude mixed-frequency activity (REM)
- Know sleep stage functions: N3 is deep slow-wave sleep; both NREM and REM contribute to memory, and dreaming is not exclusive to REM
- Understand circadian rhythm disruptions: jet lag, shift work, screen exposure effects
- Distinguish the five sleep disorders and which sleep stage each affects
- Memorize dream theories: activation-synthesis (random) vs. memory consolidation (purposeful)
- Remember REM rebound: increased REM sleep after deprivation
Free Response Question (FRQ) Tips
- Use precise terminology: circadian rhythm, SCN, hypnagogic sensations, muscle atonia, REM rebound
- Link sleep stages to functions: explain why Stage 3 is restorative and REM consolidates memories
- Apply sleep theories: describe how restoration, memory consolidation, and evolutionary theories explain sleep's purpose
- Explain sleep disorder effects: connect disorders to specific sleep stages and behavioral consequences
- Use real-world examples: jet lag effects, pulling all-nighters, sleep deprivation impacts on performance
Quick Review Summary
The Big Picture
Sleep is an altered state of consciousness regulated by circadian rhythms (24-hour biological clock controlled by the SCN). Sleep cycles through NREM stages (1-3) and REM approximately every 90 minutes. Both NREM and REM support multiple functions, including aspects of memory, while stage distribution changes across the night. Dreams may result from random neural firing (activation-synthesis) or serve to consolidate memories. Five sleep disorders (insomnia, narcolepsy, sleep apnea, REM behavior disorder, somnambulism) disrupt healthy sleep and impair daily functioning.
Essential Concepts
- Consciousness levels
- Circadian rhythm (24-hour cycle)
- SCN (suprachiasmatic nucleus)
- Melatonin regulation
- Variable recurring NREM–REM cycles; approximately 90 minutes is only a rough shorthand
- Stage 1: Theta waves, hypnagogic
- Stage 2: Sleep spindles, K-complexes
- Stage 3: Delta waves, deep sleep
- REM: Paradoxical, muscle atonia
- REM rebound
- Restoration theory
- Memory consolidation theory
- Activation-synthesis theory
- Insomnia
- Narcolepsy
- Sleep apnea
- REM behavior disorder
- Somnambulism
- Sleep deprivation effects
Sleep FAQs
Does dreaming happen only in REM sleep?
No. Dreams can occur in NREM sleep too. Vivid, story-like dream reports are especially common after REM awakenings.
Does everyone have exactly five sleep cycles?
No. Sleep duration, cycle timing and stage distribution vary. Deep NREM tends to be greater early in the night, while REM periods generally lengthen later.